
Home / Foundations of Movement
Understanding Pain Science: What Really Hurts During Rehab
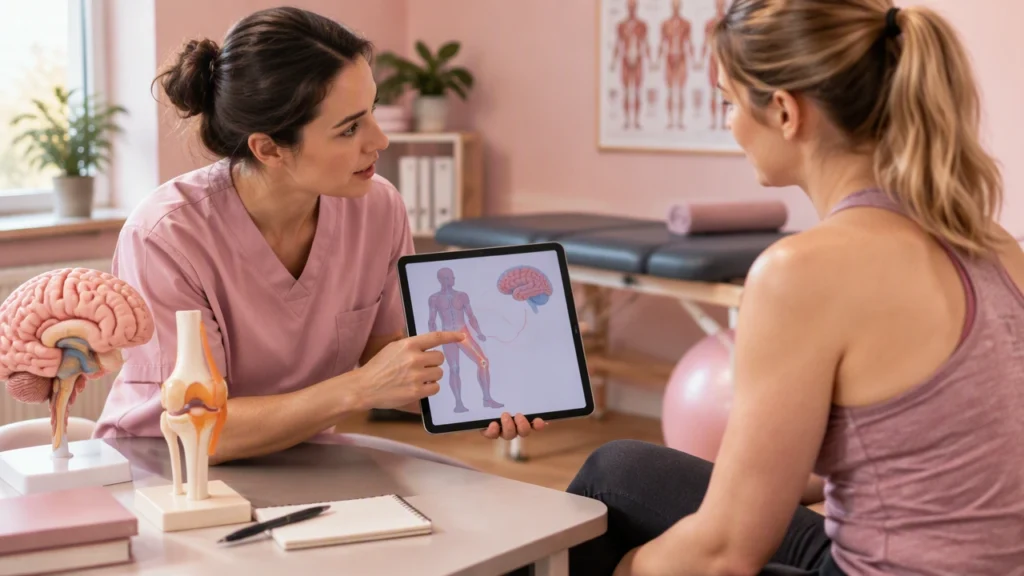
Physiotherapy education increasingly treats pain neuroscience as a core clinical skill, not an optional lecture. When people understand how the nervous system produces pain, they can interpret discomfort during rehabilitation exercises at home with more confidence and less fear. The goal is not to dismiss pain or push through it blindly. It is to develop a clearer, safer way to decide what a symptom means, when to continue, and when to adjust.
Pain is an output, not a direct damage report
A common assumption is that pain equals tissue injury. In reality, pain is a protective output created by the brain and nervous system after it evaluates multiple signals: movement, context, attention, memories, expectations, stress, and prior experiences. Tissue information matters, but it is only one part of the picture.
This distinction is useful during physiotherapy. A person may feel a strong sensation while bending, lifting, or returning to an activity even when the tissues are tolerating load well. Another person may have substantial tissue changes and feel little or no pain. Neither situation is unusual. Pain can be very real without proving that damage has occurred.
During exercise, this means the intensity of discomfort is not a perfect measuring tool. The nervous system may become more protective after periods of inactivity, poor sleep, anxiety, or a flare-up. It may also become less protective when movement feels familiar, safe, and successful. Learning to read these patterns helps people respond with skill rather than panic.
What helpful and unhelpful discomfort can feel like
Rehabilitation often includes sensations that are unfamiliar. Stretching, strengthening, and loading injured tissue can produce warmth, tightness, aching, pressure, or mild to moderate discomfort. These sensations may rise during an exercise and settle soon afterward. Movement may feel stiff at first and then easier as the body warms up.
More concerning signs include sharp or catching pain that stops movement suddenly, a clear worsening that persists for many hours afterward, new numbness or weakness, or symptoms that become progressively worse across several sessions. Pain that remains calm for a day or two after exercise is often compatible with adaptation, while pain that escalates each time usually suggests that the dose or technique needs attention.
No single sensation guarantees safety or harm. The pattern matters more than one isolated moment. A physiotherapist can help a person compare symptoms across time, identify meaningful changes, and create clear boundaries for exercise. That guidance is especially valuable when rehabilitation takes place outside a clinic.
Why explanations change behavior
Pain science explained for people doing rehabilitation exercises at home is not only about understanding biology. Explanations shape decisions. If every twinge is interpreted as new damage, a person may avoid movement, brace excessively, or stop activity before tissues have a chance to adapt. Fear can then reduce confidence, strength, and participation in daily life.
When discomfort is understood as a change in protection rather than proof of injury, movement can become more approachable. A person may think, “This is a familiar sensation, and it settles when I reduce the speed or range,” instead of, “Something has torn.” This kind of reasoning supports gradual exposure to movement and makes progress easier to measure.
Education also helps patients notice improvement beyond pain scores. Better sleep, easier walking, greater confidence, improved endurance, and fewer worries about movement are meaningful signs of recovery. Focusing only on a single pain rating can hide meaningful change.
Using pain science during home exercise
A safe home program usually relies on a few practical rules. Start with a tolerable dose, monitor the response, and adjust one variable at a time. For example, change repetitions, range, resistance, or speed rather than making several changes at once. This makes the effect of each session easier to understand.
It also helps to separate a temporary increase in symptoms from a lasting deterioration. Mild soreness during or shortly after exercise may be acceptable if it returns to the person’s usual level within a reasonable period. Symptoms that remain elevated, spread, or interfere with sleep and daily activities deserve reassessment.
Technique still matters. Pain science does not replace good coaching. Controlled breathing, stable positioning, appropriate range, and progressive loading help the body build tolerance without unnecessary strain. The aim is to provide enough challenge for adaptation while keeping the nervous system engaged rather than alarmed.
Building confidence without ignoring warning signs
Confidence grows through repeated, successful experiences. A person who learns that a manageable sensation can rise and fall during exercise is more likely to continue rehabilitation. Small victories, such as completing a walk, lifting an object, or returning to a household task, can reduce threat and make the next step feel possible.
At the same time, pain science should never be used to pressure someone into ignoring concerning symptoms. New trauma, severe or unusual pain, loss of function, fever, unexplained weight changes, or symptoms that rapidly worsen require medical evaluation. A thoughtful physiotherapist respects uncertainty and refers when appropriate.
The most useful message is balanced: discomfort is information, not a verdict. It can guide modifications without defining the entire recovery journey. With clear explanations, sensible pacing, and regular review, patients can interpret discomfort more accurately and move forward with greater confidence.
How physiotherapy education supports safer progress
Effective physiotherapy education teaches patients to ask better questions. Instead of asking whether an activity is completely pain-free, they can ask whether the response is proportionate, predictable, and recoverable. They can also track function, mood, sleep, and confidence alongside pain.
This approach gives clinicians and patients a shared language. It makes home exercise less intimidating and more adaptable to real life, where symptoms fluctuate with stress, workload, and rest. When people understand what pain can and cannot tell them, they are less likely to interpret every flare as failure.
Rebuilding movement is rarely a straight line. Pain neuroscience provides a framework for staying steady through setbacks, celebrating meaningful gains, and choosing the next step wisely. The result is not fearless movement for its own sake, but informed movement that supports recovery while respecting the body’s signals.
